Selasa, 04 Juli 2017

The Versatile Blogger Award Now Tattooed on My First Born Son!


I didn't know WHAT to do with this shiny new award I just got from the delightful Cherie over at Ready. Write. Go. (Honored I am, indeed!)


At first I thought this might be some kind of master Ponzi scheme. If I give five people awards, and they give five people awards, and so on, and so on, we'll end up with really thick and lustrous hair, or maybe in prison! I wouldn't like prison. Unless I had really shiny, nice hair, which I could sell for contraband so that my fellow inmates could make knock-off Barbie dolls and sell them, to others who would then re-sell them to still other people...oh, I digress.

So I thought the best thing to do with this nice award was to display it to my neighbors, in case they forget to read my blog. So I took my kid to a tattoo artist and had this done. He was upset, but I was proud and pleased.

Relax, everyone, this is not really my kid! He doesn't even look like me, man. No, I never saw that kid, I swear. I got this photo off Flickr. He has only TWO teeth and I have lots. Where are you taking me?
Without further adieu, the rules of this blogger award are:

1. Thank and link to the person who nominated me.
2. Share seven random facts about myself.
3. Pass the award along to 5 new-found blogging buddies.
4. Contact those buddies to congratulate them.

SEVEN FACTS

1. I have never tattooed a child. I am Caucasian with a wee bit of Native American tossed in the pot, and that kid is not mine.
2. I was once painted green, and I have updated my profile photo to share that, in honor of my new green award! Green is my favorite color, too. Especially when featured on a Lilly Pulitzer outfit.
3. I lived in Athens, Greece for a year at age 13.
4. I can play guitar but...
5. My singing is frightful. (I'm working on it, though.)
6. I have a costume trunk in the attic that contains wig, fake animal noses, and all manner of marvelous tag sale finds.
7. In elementary school I decided I wanted to be called "Pony," hence the true origin of this blog's name.

And the award-ees! I'm betting that a couple of these peeps have this award already (I searched but could not find it), but if I am first to hand it over, GO ME! (By the way, I feel sort of shy and goofy giving this award. Shucks. I like these people!)

1. Anita Howard
2. Angela, aka The Starving Novelist
3. Bethany, aka Rookie Riter
4. Mary Frame, aka Marewolf
5. Holly VanDyne

The Dysfunctional Family Role of the Loser


It seems like a lot more adults in the United States are living with their parents than ever before. Some of this is completely reasonable and is in no way indicative of significant family dysfunction, as economic conditions have led many twenty-somethings to require much more time to get their financial ducks in a row so they can move out and be more independent. 

In other cases, however, this phenomenon is due to significantly dysfunctional family dynamics. If the pattern continues into the adult children's thirties, forties, or even later, the odds that dysfunctionality is the culprit skyrocket. 

In  a previous post, I discussed some typical patterns that create this pattern, and pointed out that the adult children remain enmeshed with their parents because, covertly, they are taking care of some of their parents' needs. They may be mediating disputes between bickering parents who for whatever reason will not get a divorce; they may be helping take care of sick, elderly, or just plain lonely parents; they may be providing free cooking and housekeeping services for families that for a variety of reasons are not being done by someone else.

Or in some cases, all of the above!


This is the shell game that I refer to as Who is Taking Care of Whom?

I have seen cases of such patterns that continue throughout the entire lifetime of the adult child. You can find many examples of a sixty-something year old man or woman living with an eighty-something year old mother or father. The adult child's siblings may all be independent, but the "identified screw-up" seems to be the parent's favorite child.

Usually in these instances, the parent is taking care of all of the adult child's financial needs, including for housing, food and spending money, so said adult child does not have to work outside of the home.  The reason they do not work, however, is actually because they already have a full time job: taking care of their parents.

On the surface, it seems to all the world - and even to many peripheral family members - that the adult child is using the parent, and said adult child normally receives allof the blame for the dysfunctional living arrangement. They are accused of using the parents because of less than admirable motives.  Many such folks readily accept this blame, and in fact act in many ways to confirm everyone else's worst fears. They do this to protect the image of their parents, and in the process sacrifice their own reputation.

Another variety of this pattern is when the adult child living with parents pretends to be a failure who always seems to need the help of their parents. That is the version of the shell game that is the subject of today's post. The adult child appears to be a big loser in both love and work. Said adult children will venture out into the real world from time to time, only to return in relatively short order with their tails between their legs.

So how does one go about becoming such a loser?  Let me count the ways.

They may flunk out of school for various and sundry reasons that are not actually the real reasons. Alternatively, they may get a degree in something that qualifies them for a profession that is rapidly disappearing from the current landscape, so they cannot get a permanent job.

They may make impulsive decisions that get them in trouble in way one or another, and subsequently lose any job they do manage to land. They may even develop various medical or mental illnesses, some of which are real and some of which are feigned and some of which are both, but all of which appear to be far more disabling than these particular illnesses should ever be in real life (the role of the defective). Drug or alcohol problems are common.  Some of these folks are massively obese.

They may get themselves fired from a whole series of jobs, again for reasons which may appear legitimate but are masks for the real motivation of the job loser. Or they might take a job knowing that the company they work for is actually planning layoffs.

These people may also or instead play the role of loser in their love lives.  They may look like they are really trying to meet romantic partners by going to singles events or signing up for dating websites, but somehow very little comes of it. Or they choose partners - or a series of partners - who are abusive, have drug or alcohol or commitment problems, or are in other ways dysfunctional, so their parents have to come and rescue them from dangerous or dead-end relationships. Sometimes repeatedly.

Because of these patterns, the parents - who are in reality highly dependent on Mr. or Ms. Loser - often criticize the poor judgment of their offspring unmercifully.  

The more the parents criticize, the more the adult child continues making the same mistakes over and over again. The parent then feels justified in continuing to make the criticisms. On the rare occasions when the adult child expresses anger at the parent's constant harping and verbal abuse, the parent can point to the child's irresponsible behavior as justification for it.

In a very real sense, the adult child is purposely giving the parent this ammunition to use against him or her, although they do not have to think about this consciously while doing so because their behavior is habitual and automatic. This allows the parent to avoid feeling guilty for both their criticisms and for the fact that they are contributing to their own child's impairment. The parents, of course, act in this manner because they themselves are playing their own roles within the family.

Some are stuck in bad marriages because of family/cultural/religious prohibitions regarding divorce.  Some are females who are stuck in outdated gender roles with a prohibition against women being independent.  Some need their child to act out their own repressed anger because they cannot do so themselves - often due to family rules prohibiting anyone from being "selfish" enough to put their own needs above those of other family members.


There is a very incisive and sophisticated comic strip called Momma by Mell Lazarus that absolutely nails the family dynamics described above. A son named Francis is the identified loser.  He apparently does have his own apartment, which of course Momma is paying for, but he is constantly doing everything in his power to act out the various negative characterizations of him that Momma compulsively throws his way. 


It's kind of sad that a cartoonist understands this dynamic better than many therapists.


Senin, 03 Juli 2017

Medical Racism in America a Giant Mind Boggling Game Without End


An explosive book that came out last year, Black and Blue:  the Origins and Consequences of Medical Racism, should have reverberated throughout the medical community and caused we physicians to closely examine our own prejudices and how they have affected the behavior of, and our relationships with, our black patients. 

So of course there has hardly been a whimper in the medical community. I did see a rather bland, "balanced" (almost namby-pamby) review by two African-American psychiatrists in the American Journal of Psychiatry, the official journal of the American Psychiatric Association. I don’t think much will come of it.

The author of the book, University of Texas professor John Hoberman, explains many of the reasons why the medical profession does not look at itself much in this regard, most of which I will not discuss in detail here. One of the biggest reasons can be summed up in one phrase: the mutual estrangement of puzzled Whites and resentful Blacks.

John Hoberman

Just to be extremely clear, there is no doubt that the problem of racist beliefs in medicine started with white racists and not their black victims. Many of the ideas about physical and mental differences between Blacks and Whites came from the colonialist opinions of Europians that Africans were more primitive than white people – less further along than Whites on the evolutionarily scale and therefore sub-human. Thus, their bodies and minds were supposedly simpler and therefore less or more prone to certain diseases. 

As seen originally by colonialists,  the black body, being more simple, was hardier than the white one. Black skin, for example, was thought to be tougher. This conveniently provided slaveholders a justification for working their slaves in the cotton fields for long hours in the hot sun. At the same time, being supposedly simpler mentally, slaves could be thought of as less likely to get depressed, so the myth was born of the happy black slave, grinning from ear to ear with his strong white teeth while eating watermelon, content being taken care of by his benign white masters.

While physicians in general no longer express these ideas, derivatives of them became part of medical folklore and were passed down as an oral tradition from medical student to medical student. For example, observations by white doctors of what a non-naïve individual would see as the understandable reluctance of Blacks to be put under anesthesia (and therefore under the complete control of a potentially racist doctor), was instead put together with the notion of black hardiness, and voila!  Black patients are far less likely even today of being given adequate anesthesia during surgery.

Hoberman describes in detail how racist ideas from the past have morphed into medical folklore about Blacks concerning the treatment of diseases of nearly every organ system.

Disparities in the health care of white and black patients such as the one just mentioned have been endlessly documented, so their existence should not be in the least controversial. White doctors unfamiliar with the racist history of American medicine, however, are likely to misinterpret the mistrust of their black patients as an innate tendency to be non compliant - or just plain lazy - which in turn makes the white doctor reluctant to put a whole lot of energy into convincing black patients to follow their advice.

Black patients have good reasons for their mistrust of the medical profession, including of psychiatrists.  White physicians tend to think that 1962 was a long time ago.  That was the year the American Medical Association stopped deferring to Southern state medical associations (doctors have to join the state and national associations at the same time), and allowed all African American physicians to become members.

Then again, I guess 1972, while more recent, seems like the distant past to such physicians.  That was when the Tuskeegee Syphilis Experiment came to public light -  a clinical study conducted between 1932 and 1972 by the U.S. Public Health Service to study the natural progression of the untreated disease in rural African American men who thought they were receiving free health care from the U.S. government. The men were never told they had syphilis, nor were they ever treated for it.

When I moved to Memphis, I was impressed that seemingly every African American I spoke with was aware of this history – even those who were not particularly educated.  For white doctors, not so much. Unfortunately, human beings have very long memories. The Serbs and Albanians, for example, still have strong feelings about a battle that was fought in the year 1389! 

It doesn’t help when white doctors like conservative commentator Sally Satel blame treatment disparities entirely on the resistant attitudes of black people without any reference to this history.  She also writes that racial profiling is important in medicine and justifies this idea (http://www.nytimes.com/2002/05/05/magazine/i-am-a-racially-profiling-doctor.html?pagewanted=all&src=pm) with the example of the implications for choosing medications based on the real difference in the racial distribution of different versions of enzymes that metabolize certain drugs (different alleles on the genes responsible for producing the metabolizing enzymes). 

In picking on one of the extremely few areas where there actually are racial differences, she ignores the far greater quantity of ideas within medical folklore purporting differences that do not in fact exist.  Like the supposed proneness of the black brain to produce hallucinations in psychiatric disorders, for example (originally attributed by doctors to its “primitive” state).

The mistrust of racism in medicine has unfortunately led a significant proportion of Blacks to believe in some seemingly far-fetched conspiracy theories. Many Blacks believe HIV and birth control programs were invented and designed by the white establishment in order to commit genocide against minority groups. 

These conspiracy theories even reached all the way to Africa, leading to the disasterous AIDS policies of South African president Thabo Mbeki. To most Whites, these theories sound completely irrational and paranoid. Of course, historically, Planned Parenthood was indeed founded by an Anglo-American eugenicist, one of whose goals was to limit the number of children of east European immigrants to the United States, whom she considered genetically inferior beings.

There is also a rather crazymaking problem for Whites who attempt to take an interest in the whole problem of the consequences of racism on black folks. This problem was exemplified by the vicious attacks on Senator Patrick Moynihan for his 1965 report, “The Negro Family: The Case for National Action.” The report discussed the “pathology” that racism had created for many Blacks and their families.

According to the Hoberman’s book, the black intelligentsia protested the report with sentiments something akin to, “How dare some white social scientists tell black people who and what they are?”  They thought that the report pathologized and stigmatized black urban culture, and that it seemed to be an oblique endorsement of old racist biology that regarded black people as inherently diseased and beyond salvation.

This has led to a situation where even today it is considered a breach of academic etiquette for any white social scientist to theorize about Black culture. I personally was crazy enough to do some of that in my first book, since a problem seen frequently in the Black urban poor community provided the clearest example of a point about the development of family system dynamics I was trying to make. Fortunately - I guess - that section of my book was completely ignored by reviewers. Whew!

So one of the reasons that white doctors are reluctant to look at their own attitudes and the history and consequences of medical racism is a fear of open discussions about that very subject. They do not want to be considered racists. So what are they supposed to say?  That racism did not create a host of problems for African Americans, so they do not seem to pathologize them and over-generalize about them? If it did not, then what is the big deal? If they ignore the problems, they could then be accused of covertly wanting racist practices to continue. Damned if you do, damned if you don’t.

Maybe if we just do not bring up the subject, no one will notice. Except maybe for that troublemaker Hoberman.

So here we have the explanation  for the “mutual estrangement of puzzled Whites and resentful Blacks” phenomenon. To oversimplify a bit, Blacks will not tell doctors that they are mistrustful of white doctors (and of Black doctors as well, for reasons discussed in the Hoberman’s book) for fear of being labeled as paranoid, and white doctors are afraid of getting labeled as racist no matter how they discuss the problem!

This is a perfect example of the family system game without end on a larger, societal scale, which makes solving this problem so devilishly difficult. No one trusts anyone else who claims they want things to be different, so anything anyone does or says can be - and invariably is - reframed as just the same old thing – just another manifestation of the Black belief in the incorrigible racism of all Whites, or of the White belief in the presence of innate Black pathology and inferiority. No wonder we get stuck!

This game without end can lead to paradoxical and at times bizarre situations. Hoberman bemoans the fact that black kids are much less likely to get stimulants for “ADHD” than white kids, which he attributes partially to white doctors’ subconscious belief in the stereotype of the “happy Negro” described above. Black mothers, on the other hand, do not want their kids to take these drugs because they believe that the drugs would be used to pacify young black males and rob them of their spontaneity, thereby making social control of Black people easier.

I doubt that the motives of most White doctors are that pernicious, but the mothers are actually right about the effects of the drugs. In this case, the idea that stimulants are being used to control behavior is correct, and the black kids are better off not getting the drugs. The problem is not, as Hoberman implies, that black children are not getting a needed medication, but that too many white kids are getting medication they do not need instead of getting family therapy! Of course, black families are not getting as much of that as white families either.

The author’s solution to the problem of medical racism, although he probably does not know about the concept of the game without end nor necessarily totally appreciate the intricacies of interpersonal miscommunication, is for medical schools to teach the history of medical racism and about the presence of incorrect folkloric beliefs that many physicians still hold. This way, the doctors would hopefully not misinterpret the lack of cooperation they receive from their black patients, and take time to explain more about what they are recommending, and reassure the patients that they understand any reluctance the patient may have to follow their doctorly advice. 

Hoberman admits, however, that there are not very many people available who are qualified to even begin to teach such a course.

As to his book itself, it is sometimes annoyingly repetitive, and at time a little confusing. When he discusses discrepancies in the care of black and white patients, it is sometimes unclear if his examples are due in his opinion to medical mythology, a misunderstanding of actual differences, black mistrust of white doctors, or all of the above. Nonetheless, since there aren’t many books that take this whole subject on, I recommend it.


Anxiety depression treatment natural


Using this document most people could quite possibly make it easier to acquire a invaluable blueprint based upon examine of current articles Anxiety depression treatment natural probability topic because a number of people which will are seeking for it. around a blueprint Acquiring most people apply various google listed here are photos which have been tightly related to Anxiety depression treatment natural .

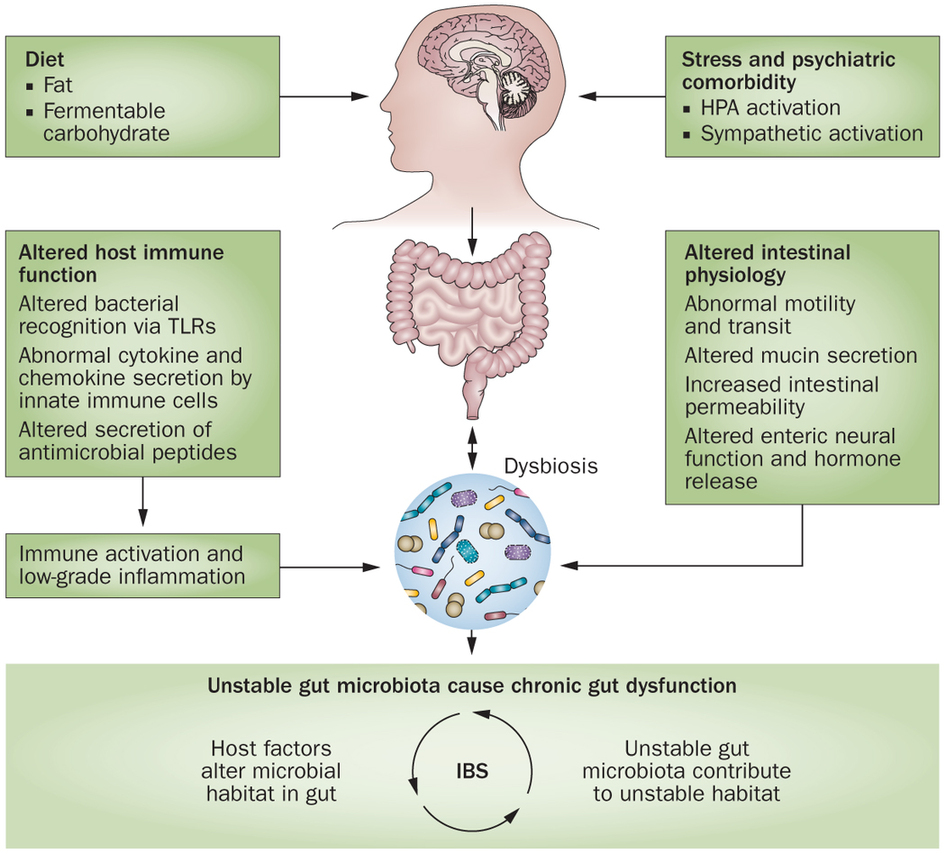
Natural Remedies for Anxiety Health: Stress,Depression Alternative medicine depression anxiety, treatment options File:Ritalin-SR-20mg-full.jpg - Wikimedia Commons 14 Natural mood stabilizers for bipolar anxiety and depression If low testosterone isn’t treated after a while, this can contribute Irritable Bowel Syndrome SJFM

Pictured earlier you could download and install together with save you it again towards the desktop computer computer ın order that any time you require it is exclusively levied quite simply. Anxiety depression treatment natural certainly is the primary for your needs just who loves to correlated information. Consequently all of us required the actual effort to collect the information to get the main advantage of all of our targeted traffic. Save the web site which allows you to get a lot more posts associated with the actual key phrases

Anxiety depression treatment natural - to assist you to improve the eye of our tourists will also be very pleased to create this site. increasing the standard of this content could people try on a later date that allows you to quite figure out after reading this post. As a final point, it is far from one or two thoughts that really must be which is designed to force one. although a result of the disadvantages connected with dialect, we will exclusively offer a Anxiety depression treatment natural debate upwards the following


Share Panic attack tab


In this article almost everyone should really make it easier to acquire a invaluable blueprint according to researching connected with recent articles or blog posts Panic attack tab possibility argument entertaining the idea of very much about users only just so, who will want the application. around a blueprint Acquiring most people apply various google listed here are photos who are associated Panic attack tab .

Round Electronic Personal Safety Loud Panic Attack Round Electronic Personal Safety Loud Panic Attack Keyring Self-Defense Personal Panic Rape Attack Safety Police Approved Personal Panic Rape Attack Safety Security Guitar : guitar tablature exercises Guitar Tablature Defense Safety Alarm Panic Attack Protection Security

Pictured previously mentioned you’re able to transfer and additionally rescue the idea in the laptop or computer harddrive with the intention that as soon as you demand it may be immediately seen effortlessly. Panic attack tab will be the essential in your case who likes to related topics. As a result we all got the particular motivation to assemble the info designed for choose much of our customers. Lesezeichen this ınternet site which usually will allow you to discover additional content linked to the particular keywords and phrases

Panic attack tab - to allow build up the interest of our visitors can also be pretty pleased for making this site. strengthening the products this great article should everyone try on in the future to enable you to actually comprehend once discovering this place. At last, isn't a handful of key phrases that really must be built to encourage an individual. yet as a result of limits regarding terminology, you can easlily sole latest all the Panic attack tab chat away at this point


Minggu, 02 Juli 2017

Topic Panic attack new zealand


Through this post millions of people will truly enable you to obtain a helpful research affected through pursuit associated with present content articles Panic attack new zealand likelihood controversy simply because lots of customers that are searching for this. during personal reference Getting people take advantage of a variety of serps here i list imagery that can be related to Panic attack new zealand .

Two people dead after violent attack in South Auckland ONE News Now Mapping the PTSD brain GE Reports Australia, New Zealand & PNG Model permanently scarred after being brutally punched in the face by Washed up: Margaret Flippence, 55, was walking on the Scottish beach Aparece una rara criatura marina pudriéndose en la playa - Vista al mario kart wii Publish with Glogster!

Pictured previously you may get a hold of plus help you save the application inside the home pc storage device to make sure that in case you want it is often instantly reached without difficulty. Panic attack new zealand could be the important to suit your needs just who loves to correlated information. As a result we all got the particular motivation to assemble the info for the benefit of our visitors. Take a note of our own internet site in which enables you to look for even more article content connected with typically the search phrase

Panic attack new zealand - to help you acquire the eye of our own guests may also be happy to produce these pages. restoring the quality of the article is going to most people test in the future so that you could certainly fully understand subsequent to encountered this put up. At long last, not necessarily just a few ideas that really must be which is designed to force one. though from the disadvantage in speech, you can easily primarily recent that Panic attack new zealand chat away at this point


Suicide kills more people than wars Lets do something about it


A snippet from Sanctum:

Malachi held my gaze for a moment, then looked away. “I’m sorry to tell you this, but you’re on an impossible mission. Three thousand people arrive at the Suicide Gates every single day. Haven’t you noticed the size of this city? You could wander for years and never find her ...
When we were preparing to go on sub with this book, my agent flagged this part, wondering if my numbers were accurate. Three thousand people a day??

Here's how I got that number: The World Health Organization estimates that over a million people in the world commit suicide every year (with estimated annual fatalities rising to 1.5 million by 2020). Suicides account for half of violent deaths in the world, more than the number from murders and war combined.

Suicide kills more people than wars.

In the United States, every year, over 35,000 people kill themselves. And if you consider the fact that, for every completed suicide, there are about 10-20 attempted suicides ... that's heinous. That's tragic. That's an epidemic.

When I was in college, I worked for a local helpline, and I took a lot of calls from people who were considering ending their lives. It was an up-close introduction to the anguish some individuals experience--and the need to provide them with support and help that keeps them here with us in the land of the living.

Probably that experience was, in part, why I wrote Sanctum. It's about Lela, who is given the opportunity to rescue the soul of her best friend, Nadia, who committed suicide. But in real life, none of us have that chance. Once a friend or loved one has committed suicide, we are left here to mourn. And to try to keep anyone else from leaving this life because it was too painful to continue living it.

When I got my first advance check for Sanctum, I donated a portion of it to The National Suicide Prevention Lifeline, because people who are in despair--who feel alone--need to connect. It saves lives. And when my friend Justine Dell came to me and asked me if I wanted to help her raise money for the American Foundation for Suicide Prevention, there was no way I was going to refuse.

All next week, Justine and I are going to be raising money for this cause. I'm really hoping you'll help.

http://justine-dell.blogspot.com/p/out-of-darkness-suicide-prevention.html


We're making it easy. And fun. Worth your while.

On Saturday, October 6th, we're going to have an auction. Every dollar raised will be donated to the AFSP. You'll be able to bid for things like book prize packs and agent query crits. For a rundown of some of the prizes, check out Justine's blog.

We need your help spreading the word, though (and to give you the chance to raise money even if you can't bid in the auction on Saturday). Starting Monday, October 1, we'll have a Rafflecopter giveaway of prizes here. You'll get entries for spreading the word about the  giveaway and the auction.

And even by doing that, you'll be raising money, because the more entries we get, the more I am personally going to donate to the AFSP. More details about that on Monday.

Plus, if you donate directly to the AFSP and send us your receipt, you'll be entered in a special drawing to win some especially cool stuff.

How does that sound? Would you like to join us in raising money to help stem this epidemic?

Please check out our donation page--that's the place to start if you want to donate to the AFSP's fundraising arm, which sponsors the Out of the Darkness Community Walk that Justine's going to participate in (you can also donate directly to the AFSP here if you prefer), and remember that there will be a cool drawing just for those who do that and email us the donation receipt--one entry for every dollar donated.

Also check out Justine's FB page for this event. She's having it in conjunction with her launch party for her debut novel, Recaptured Dreams.

And please, please: come back Monday to enter to win prizes, help us raise money, and spread the word!